

News|Videos|November 14, 2024
Considerations for Discharge
Author(s)George Sakoulas, MD
Sakoulas offered his insights for when he considers discharging patients and strategies to avoid readmission.
Advertisement
Contagion: There has been data to demonstrate cefteroline response in community acquired bacterial pneumonia can be as early as 72 hours. What is the clinical significance of this and what does that mean for hospital discharge and the potential economic impact?
Sakoulas: The faster a patient improves, the sooner they can be discharged, potentially transitioning to an oral agent or even completing therapy altogether, depending on their circumstances. We’re now moving toward shorter therapy durations for straightforward community-acquired pneumonia, typically five to seven days. So, if a patient has already received three or four days of antibiotics in the hospital, they may not even need an oral antibiotic upon discharge. This minimizes exposure to additional medications.
Quick response time is critical, not only for discharge but also because patients who respond more rapidly tend to have a lower risk of readmission. Slow responders—those who are still not improving significantly after four or five days—are more likely to be readmitted. This ties back to the analogy of a slippery surface: if a car is still sliding after the brakes are applied, it’s likely to encounter more problems stopping. In the same way, shortening a patient’s response time may reduce their likelihood of readmission.
We see a similar concept with endocarditis. For example, if a patient undergoes valve replacement surgery and their cultures are negative at the time, their prognosis is generally better than if they have a positive culture during surgery, which also extends their required treatment duration.
Although readmission rates are heavily influenced by comorbidities, it remains to be studied whether a more aggressive approach with patients who have comorbidities could shorten their response time and, ultimately, reduce their chances of readmission. Nonetheless, it’s logical to aim for faster recovery to facilitate earlier discharge, benefitting both patient outcomes and hospital efficiency.
Contagion: What are some of the other risk factors for readmission?
Sakoulas: Age is definitely a major factor, especially for those over 65, as it increases risk for nearly everything. Other main risk factors include structural lung disease, diabetes, and heart disease, which can impact respiratory function. Among these, diabetes is particularly notable. A well-controlled diabetic is very different from a patient with a hemoglobin A1c in the double digits; the latter is functionally neutropenic, making bacterial infections especially challenging to manage.
Contagion: what should be the plan for discharge so you don't see readmission for these individuals?
Sakoulas: This is always a challenge. The goal is to cover as much ground as possible with therapy while the patient is a captive audience in the hospital. By using the most potent therapy available during their hospital stay, we hope to prevent infection from spreading, which may reduce complications and follow-up needs once they leave.
Additionally, there’s value in optimizing antibiotic dosing, especially for specific populations. For instance, a recent study at our hospital found that obesity is a risk factor for outpatient parenteral antimicrobial therapy (OPAT) failure and readmissions. Unfortunately, many antibiotic dosing studies have not adequately addressed the obese population. A study published in AC earlier this year (April) provided insights into more appropriate dosing strategies for obese patients. This is worth exploring because these patients may not be receiving enough of the drug to effectively treat the infection.
In summary, ensuring appropriate dosing—especially for obese patients—and using the most potent therapy possible, along with strong follow-up care, can help address issues early and potentially prevent a small problem from escalating into one that requires hospitalization.
The conversation was edited for grammar and clarity.
Advertisement
Related to this article

In the first episode of our new series looking at the food safety network, Lynette Johnston, PhD, offers insights into how the federal government surveillance infrastructure operates and how epidemiologists serve as food detectives in determining bacterial pathogens and potential foodborne outbreaks.

Food expert Lynette Johnston, PhD, provides some context around the ongoing outbreak, discusses prevention, and compares 2026 food recalls with previous years.

The Peggy Lillis Foundation will host its 17th Annual Changing the Odds Gala this month in New York City, and it will include a casino, fellowship amongst the C diff community, and an award ceremony honoring a physician-scientist, philanthropist, a researcher, and a patient advocate for their contributions to C difficile awareness, treatment, and prevention.

Resistance-guided testing targeting a single gene mutation could let clinicians safely reintroduce ciprofloxacin for the majority of gonorrhea cases still susceptible to it, sparing ceftriaxone as resistance climbs worldwide. Lao-Tzu Allan-Blitz, MD, MPH, offers insights into his work in this area.

In the third episode of the series with Perry N. Halkitis, PhD, MS, MPH, he discusses how human behavior as well as other factors play a significant role in repeating outbreaks.

The federal agency is investigating four active outbreaks linked to food and animal contact.
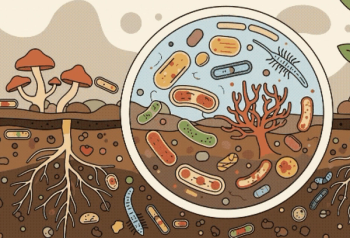
Widespread antimicrobial use disrupts vital microbial communities that regulate Earth’s biogeochemical cycles, driving antimicrobial resistance, worsening human and environmental health, and significantly contributing to climate change.

The latest CDC numbers show a 5.4% increase of measles cases from week-to-week. This year has already become the worst for the number of measles cases in the US since the disease was declared eliminated in 2000. With the start of respiratory virus season, case numbers are expected to continue to increase significantly.
Advertisement
Advertisement